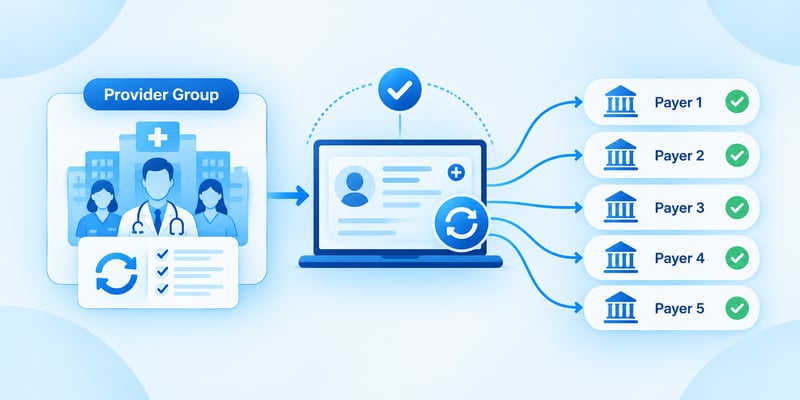
When a physician moves from one suite to another in the same building, the change takes a few seconds to enter in your credentialing system. Getting it to every payer you bill can take weeks, because each plan wants it in its own roster template, through its own portal, or in response to its own attestation request, and many never confirm that the update was loaded.
CMS's own National Provider Directory team states that providers update roughly 20 systems every month with the same information. For a multi-site group or health system, that number climbs quickly, and every system that falls behind becomes a directory error, a misrouted patient, or a denied claim. Provider data updates across payers stay manageable only when the update process is designed for many recipients from the start.
Why Is Keeping Provider Data Current Across Payers So Hard?
Keeping provider data current across payers is hard because each payer collects the same change through its own roster format, portal, or attestation cycle, so one update becomes many separate submissions. Few payers confirm that a change was loaded, so errors surface only when members or claims find them.
Three structural issues make the work heavier than it looks:
- Template sprawl: Large health systems can maintain well over a hundred roster templates for a few dozen payers, and templates often differ by product or region even within the same payer brand
- Different clocks: Commercial plans, Medicare Advantage plans, Medicaid managed care plans, and CAQH each run their own verification and attestation schedules
- No confirmation loop: Rosters go out, but many payers never send back a receipt or load status, so your team cannot tell an applied update from a missed one
Which Provider Changes Most Often Go Stale?
The changes that cause the most trouble are the ones that happen often and must reach several systems at once. The table below shows where each one needs to go and the timing rules that apply.
|
Change
|
Where it needs to go
|
Timing rules to know
|
|
New practice location or suite
|
Every payer's roster or portal, CAQH ProView, PECOS, NPPES
|
Medicare requires practice location changes within 30 days under 42 CFR 424.516, and NPPES updates are due within 30 days
|
|
Provider leaves the group
|
Every payer, PECOS reassignment, CAQH
|
Report promptly so payers can remove the listing; Medicare Advantage plans must reflect changes within 30 days of learning of them
|
|
Panel status, such as no longer accepting new patients
|
Every payer's directory, CAQH
|
The No Surprises Act expects providers to report material changes, and plans must update within two business days of receiving them
|
|
Telehealth availability added or dropped
|
Every payer's directory, CAQH
|
Treated as a material directory change by most plans
|
|
Name, TIN, or group affiliation change
|
Every payer, often as a new enrollment or contract update, PECOS, NPPES
|
Can require re-enrollment, so start early to avoid a gap in billing
|
The panel status row deserves extra attention. In Atlas Systems' proprietary 2025 Member Experience Monitor, conducted with GBK Research, 49% of members who found a directory error discovered that a provider was not accepting new patients, which makes it one of the errors members notice most.
What Do Payers Require, and When?
Payer requirements come from federal law, CMS rules for Medicare Advantage and Medicaid, and CAQH's attestation cycle, and they are getting stricter.
- No Surprises Act: Providers must give plans directory information when a network agreement starts, when it ends, when material changes occur, and on request. Plans must verify directory data at least every 90 days and update it within two business days of receiving changes
- Medicare Advantage: Plans must reflect changes within 30 days under CMS-4208-F2 and publish directory data on Medicare Plan Finder. From plan year 2028, the REAL Health Providers Act requires verification at least every 90 days and removal of departed providers within five business days
- Medicaid managed care: Plans must update electronic directories within 30 days of receiving updated information, under 42 CFR 438.10(h)
- CAQH ProView: Providers re-attest their profile every 120 days, but an attested profile does not automatically update every payer's directory or claims system
The practical effect for provider organizations is more frequent attestation requests. As plans move to 90-day verification, your office staff will hear from each payer more often unless your organization sends accurate updates first.
A Single Update Workflow for Provider Groups
A repeatable workflow turns one internal change into accurate updates for every payer, and it rests on four habits.
Keep one internal source of truth
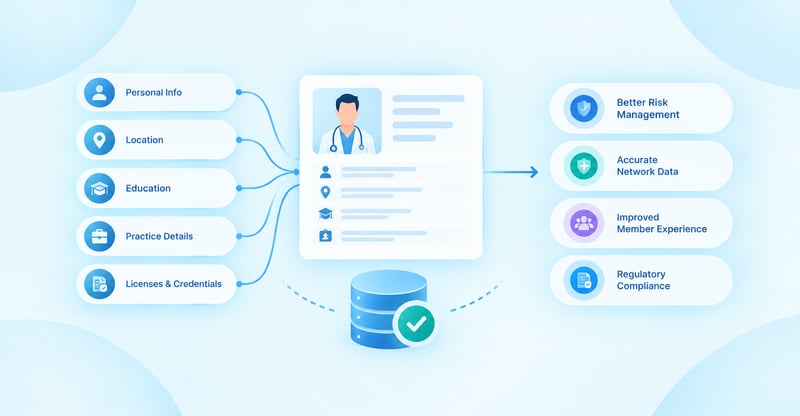
Choose one system to hold the authoritative provider record, and feed it from your EHR, credentialing, billing, and enrollment systems instead of letting each one keep its own version. Decide which source wins for each field, such as the credentialing system for license data and the practice for office hours, so conflicts resolve the same way every time.
Map each payer's roster format once
Build a mapping for every payer template, including product and regional variations, and reuse it every cycle. When a payer changes its template, update the mapping once instead of rebuilding the roster by hand.
Send changes, then reconcile the full roster
Compare your current roster with what you last sent each payer, so you can see every addition, change, and termination before submission. On a regular cadence, compare each payer's directory or roster back against your record, because that is the only way to catch updates a payer missed or applied to only some of its products.
Track confirmations, not submissions
Record whether each payer acknowledged and loaded every update, and how long it took. Consider a group that tracks load turnaround by payer for one quarter: the data usually shows which plans need follow-up calls and gives your payer relations team evidence for those conversations.
What Payers Can Do to Lighten the Load
Health plans benefit directly when provider updates arrive clean and on time, and a few changes on the payer side make that far more likely.
|
Payer practice
|
Why it helps provider groups
|
|
Confirm receipt and load status for every roster
|
Lets groups stop chasing updates by phone
|
|
Accept one roster layout across products and regions
|
Removes duplicate templates within the same payer
|
|
Share directory discrepancies back with the group
|
Turns verification into a joint fix instead of a request for more attestations
|
|
Exchange data in both directions through APIs
|
Replaces monthly files with near real-time updates
|
Plans that move toward bi-directional provider data exchange spend less on outreach because the providers' own systems keep the directory current.
How PRIME® Connects Provider Groups and Payers Through One Roster Process
PRIME® gives provider organizations one provider record and one roster process that delivers each update to every payer in the format that payer requires. The same platform supports health plans on the receiving side, so updates move in both directions without separate tools.
With PRIME® Provider-Payer Roster Management, your team can:
- Consolidate provider data from EHR, credentialing, billing, and CRM systems into a single record
- Compare the current roster against prior submissions to identify every addition, change, and termination automatically
- Convert one validated dataset into each payer's designated roster template and submit it
- Compare your records against health plan rosters to find discrepancies, then push updates such as specialty changes and retirements
- Track each payer's response time and load turnaround on a payer performance dashboard
Atlas reports that PRIME® saves up to 85% of the staff time spent on provider roster updates and reduces claim denials by up to 95% through better provider data accuracy.
Making Provider Data Updates Across Payers Routine
Provider data updates across payers become routine when one internal record drives every submission, each payer's format is mapped once, and confirmations are tracked as carefully as submissions. With Medicare Advantage plans moving to 90-day verification in 2028, the organizations that send clean updates first will spend less time answering attestation requests.
To see how this works in practice, explore provider roster submission and multi-state provider roster management, review the plan-side obligations in our No Surprises Act provider directory guide, and learn how PRIME® works as a provider data management platform for both sides of the exchange.
Get a demo today!